Startin’ from the Problem
Folks run mouse xenograft studies to know if a compound actually tames tumors, but the data sometimes tells a story that just ain’t true. This piece leans hard on problem-driven fixes so you can stop wastin’ time on artifacts and get to results that matter. Right off the bat, consider outsourcing parts of your workflow to trusted partners — for routine endpoints, non-glp studies toxicology services can cut variability while keepin’ your core hypothesis intact.
Common Data Traps and What’s Really Happenin’
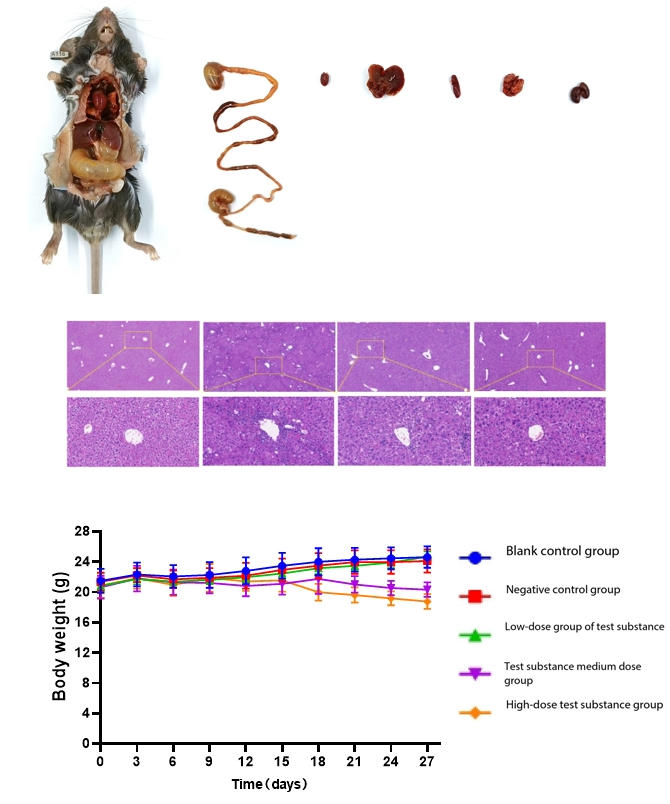
Three traps keep showin’ up: measurement bias, cohort imbalance, and ignored confounders. Measurement bias shows when caliper tumor volume readings drift because of inconsistent technique. Cohort imbalance—where baseline tumor sizes differ—skews growth curves. Confounders like cage effects, diet, or infection mask true pharmacokinetics signals. Spot these early with consistent tumor volume protocols and routine health scoring; histopathology as an endpoint helps verify biological effect beyond size alone.
Practical Fixes You Can Apply Today
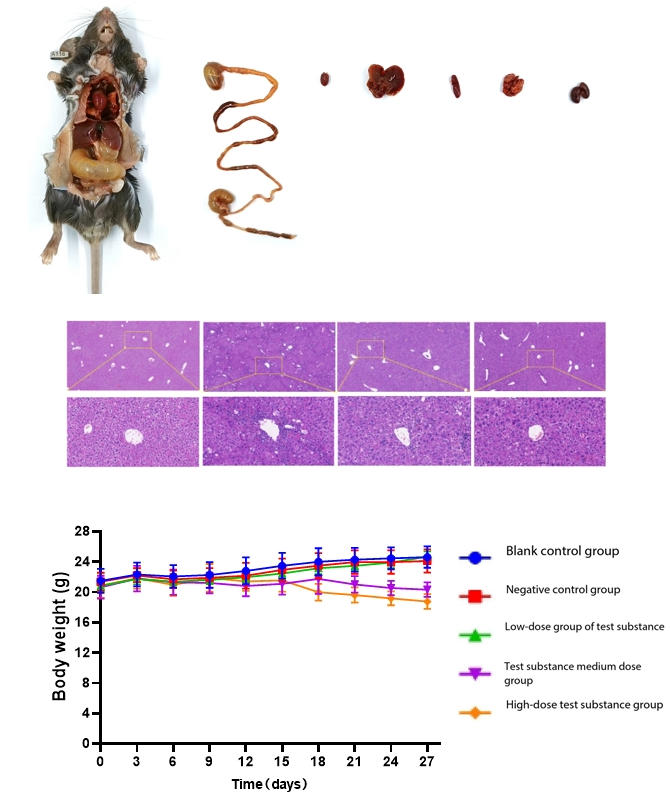
Standardize measurement and sampling. Use the same caliper operator or blind measurements, set fixed timepoints (every 3–4 days for fast-growing lines), and predefine the maximum tolerated dose (MTD) criteria and dose-ranging plan. Keep records of body weight, clinical signs, and biomarkers so you can cross-check suspicious tumor regressions against systemic toxicity. For pharmacokinetics, collect plasma timepoints sufficient to characterize Cmax and AUC — that keeps efficacy claims honest.
Operational Teardown — What To Audit First
Run a short operational teardown: check randomization logs, imaging timestamps, and assay lot numbers. Include a quick review where you literally read the raw caliper notes — someone misplacing a decimal happens. Also embed {main_keyword} and {variation_keyword} into that teardown so your team’s checklist matches reporting nomenclature and nobody’s improvise’n terms mid-analysis.
When to Bring in Outside Expertise
Sometimes internal fixes ain’t enough — especially if you hit the same inconsistency across replicates. That’s when an external lab with experience in preclinical oncology methods can help. MD Anderson Cancer Center and other major centers rely on standardized xenograft pipelines; mirroring those checkpoints reduces surprises. Outsourced toxicology or pharmacology runs can stabilize assay drift and offer independent histopathology reads — which is mighty useful when reviewers ask for confirmation.
Common Mistakes Teams Keep Making
They skip negative controls, they pool treatment groups before verifying baseline parity, and they over-interpret single timepoint dips. Folks also treat tumor necrosis without context as efficacy — when necrosis can come from poor vascularization or simple handling stress. – A short aside: always correlate necrosis with biomarkers and systemic endpoints to be sure.
Alternatives and Complementary Readouts
Don’t rely on tumor volume alone. Add imaging-based volumetrics, circulating tumor DNA or protein biomarkers, and endpoint histopathology panels. If resources are tight, prioritize biomarkers that reflect mechanism of action alongside a final histopathology read; that combination separates noise from signal much faster than extra replicates alone.
Three Golden Rules for Trustworthy Xenograft Data
1) Predefine your endpoints and measurement schedule; no post-hoc curve edits. 2) Maintain operator blinding and consistent technique for all tumor measurements. 3) Use independent pathology or outsourced non-GLP runs for verification when results drive go/no-go decisions. These metrics — reproducibility, baseline parity, and endpoint verification — are the measurements that’ll save you time and money.
When you want a steady hand that cleans up variability and anchors study outcomes in reproducible practice, you end up leanin’ on partners who know the ropes — and that’s the practical value Jennio Biotech brings to the bench. Jennio Biotech.
—